Search This Blog

Tuesday, November 16, 2010

Pulmonary renal syndrome

In rheumatology morning report today we discussed an older woman presenting with hemoptysis and acute kidney injury with a Cr in the 700s. This lead to an interesting discussion of the many systemic disorders that can present with renal and pulmonary manifestations.

Pulmonary renal syndrome is essentially the simultaneous occurrence of both glomerulonephritis and diffuse alveolar hemorrhage. This usually manifests as a rapidly rising Cr, hematuria, and shortness of breath/cough/hemoptysis/desaturation. However, we must also remember that other conditions may cause acute kidney injury and pulmonary manifestations as well (ie acute kidney injury from prerenal failure or ATN complicating pneumonia, ARDS/AKI from sepsis/trauma, malaria, rapidly progressing AKI in CHF, etc). What really is needed to differentiate these entitities from true pulmonary renal syndrome is the presence of alveolar hemorrhage on bronchoscopy and the presence of glomerulonephritis on biopsy or urine microscopy (hematuria, red cell casts).

The causes of pulmonary renal syndrome include:

Connective Tissue Disorders

Polymyositis or dermatomyositis

Progressive systemic sclerosis

RA

SLE

Anti-glomerular basement membrane disease

Goodpasture's syndrome

Systemic Vasculitidies

Behçet's syndrome

Churg-Strauss syndrome

Cryoglobulinemia

Henoch-Schönlein purpura

Microscopic polyarteritis

Wegener's granulomatosis

Other

Drug Reactions

We discussed that the initial workup for these patients should include CBC + diff (for cytopenias), smear (for hemolysis), Cr, BUN, Lytes, Ca, Mg, PO4, albumin, LFTs, INR, PTT, CXR, EKG, and urinalysis and microscopy.

Further serology should include:

ANA, dsDNA if ANA positive (for SLE)

ANCA (c-ANCA (anti-PR3) positive in Wegener's, p-ANCA (Anti-MPO) in microscopic polyangiits, P>C-ANCA in Churg-Strauss. (Note: immunofluorescence is sensitive but less specific while ELISA is specific and sensitive. Know which one your lab does.)

Anti-GBM for Goodpasture's

Definitive Diagnosis: biopsy of lung/kidneys.

It is often necessary to make quick but definitive diagnoses as the consequences of not treating are dire, but the side effects of many of our immunosuppressive agents are not insignificant.

Please see a post from July on an interesting case of levimasole-induced vasculitis.

See here for an interesting review of ANCA vasculitidies from 2009.

Tuesday, November 9, 2010

Varicella & Pregnancy


Last week we discussed a case of an immunosuppressed woman with herpes zoster infection of the face, and the concerns that go along with that (what to do with her immunosuppressive medications? Ophthalmalogic concerns? Differential diagnosis). Today, we discussed a woman visiting from sub-Saharan African with a diffuse vesicular rash, ultimately thought to be disseminated varicella with varicella pneumonia. A surprise to everyone - someone wisely ordered a BHCG and she was, in fact, pregnant.

The CDC "Pink Book" has a wealth of information on many vaccine preventable illnesses - easily found by googling "CDC Pink Book". Looking under varicella, there is access to pictures, literature, vaccine recommendations, and more. Here is the link.

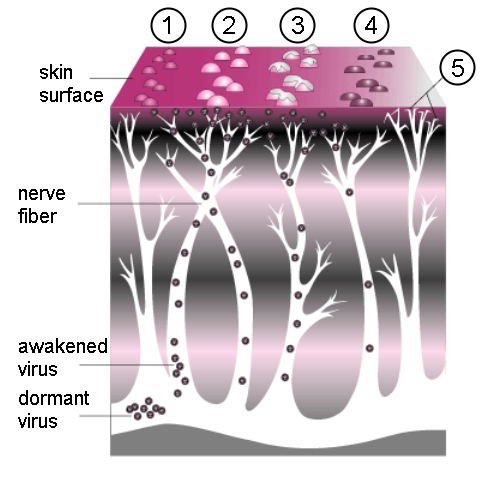
Varicella zoster virus (VZV) is a member of the herpesviridae family responsible for both acute infection ("chickenpox") and recurrent infection (herpes zoster, or "shingles"). After primary infection, VZV persists in sensory nerve ganglia and can result in recurrent infection, especially in immunocompromised hosts. It is transmitted through the respiratory tract (airborne & contact precautions in most hospitals!) with an incubation period of 14-16 days, although longer in immunocompromised hosts. Primary infection, as in our patient, is usually preceded by a 1-2 day malaise, followed by a generalized, pruritic rash that progresses from macules, to papules, to vesicular lesions, then crusts. Lesions of all ages can be found. Recurrent infection is more common in those with immunosuppression, advanced age, intrauterine VZV exposure, and VZV infection at less than 18 months. Zoster can become disseminated and involve the skin, CNS, lungs, and liver. It typically involves the fifth cranial nerve (as in our patient last week) or the trunk.

Complications can be severe, and can include:
  • Secondary bacterial infection of skin lesions
  • Viral or secondary bacterial pneumonia
  • Meningitis or encephalitis (especially affecting cerebellum, leading to ataxia)
  • Reye syndrome
  • Myocarditis, GN, Transverse Myelitis, TTP, adrenal insufficiency
  • Congenital Varicella Syndrome (CVS)
Congenital Varicella Syndrome is a risk if infection occurs in the first 20 weeks of gestation. Risk is actually pretty low (2%). It is manifest by:

  • Low birth weight
  • Hypoplasia of an extremity
  • Skin scarring
  • Localized muscular atrophy
  • Encephalitis, cortical atrophy, chorioretinitis, and microcephaly

CVS is distinct from the risks if mum develops VZV from 5 days before to 2 days after delivery, which can result in overwhelming neonatal infection and 30% fatality rates. This is thought to be the result of fetal exposure without passive maternal antibodies.

We consider VZIg in certain populations, including:

  • Immunocompromised patients
  • Neonates whose mothers have signs and symptoms of varicella around the time of delivery
  • Preterm infants born at or greater than 28 weeks gestation who are exposed during the neonatal period to non-immune mums
  • Preterm infants born at less than 28 weeks' gestation or who weigh 1,000g or less at birth and were exposed during the neonatal period, regardless of maternal history of varicella disease or vaccination
  • Pregnant women within 96 h of exposure
A few final pearls:
  • All pregnant women should receive treatment (ie with acyclovir). See here for an article on management of VZV in pregnancy.
  • Don't forget to consider other possibilities: Measles? Coxsackie? Impetigo? See here for some pictures and a summary table.
  • Lastly, we must remember that geography plays a large role in varicella immunity. Many immigrant and refugee populations come from tropical and subtropical climates, where varicella immunity is much LOWER than in temperate climates like ours. Thus, a pregnant mum hailing from Zambia is a lot less likely than one born in Toronto to be immune to VZV. Given the risks, we should perhaps be engaging in routine antenatal screening of women from tropical/subtropical zones and providing vaccination, as well as insuring that they have access to timely and appropriate antenatal/pre/postnatal care. There has been some study on this issue, and here's an example.

Thursday, November 4, 2010

Low Back Pain


Today we discussed a common presentation but difficult dilemma: chronic low back pain, with new neurological symptoms. When do you know to investigate further? How do you manage complex pain? What are the red flags? What is an anatomical approach to neurological manifestations? We discussed many of these issues today. For the internist, it is often important to be able to differentiate inflammatory from mechanical back pain.

It's worthwhile discussing the differential diagnosis of back pain, which includes:
Mechanical
  • MSK injury
  • Degenerative discs & facet joints
  • Anatomic anomalies (scoliosis, spondylolisthesis)
Neurological
  • Disk herniation, with irritation of adjacent nerve roots
  • Spinal stenosis
Non Mechanical Spinal
  • Malignancy (primary or secondary) with or without cord compression
  • Inflammatory: Ankylosing spondylitis (& other seronegative spondyloarthropathies), RA
  • Infectious: osteomyelitis, epidural abscess
Visceral radiation (pelvic, kidney, GI tract, aorta)

Remember that there are several key elements to a thorough back examination:

Inspection: anteriorly (looking for alignment), posteriorly (looking for asymmetry, deformity, rashes, etc), and laterally (for kyphosis, lordosis). Also inspect their gait.

Range of motion: Assess flexion, extension, rotation, and lateral bend while standing, looking for limitation & pain. From the seated position, test rotation of the spine at the thoracolumbar region - limitation is an early indicator of inflammatory back pain.

Palpation: of spinous processes and paraspinal muscles for pain or spasm.

Special Tests: compression test (of SI joints) with patient on side, FABER test, Gaenslen's test, Book test with patient supine (pressure over both trochanters.
Other special tests to differentiate between mechanical and inflammatory back pain include the straight leg raise (positive in mechanical), femoral stretch test, the occiput to wall test, the Modified Schober, and the

A full neurological examination should accompany this exam, including a DRE to assess for sphincter tone if cord compression is suspected.

See here for an excellent BMJ review.

Wednesday, November 3, 2010

Mental Health, Incarceration, and COPD


Thanks to Dr. Sargeant for an interesting morning report today, allowing us to explore some of the more complex issues affecting our patients with mental health concerns, including their disproportionately high representation in the prison system. The causality of this relationship is complex, and often influenced by confounders like addiction, but ultimately we have to look at this as a matter of public policy and how Canada (and other nations around the world) have chosen to allocate resources. I found an interesting resource document (here) from the American Psychiatric Association that discusses some of the broader factors and implications of the relationship between mental illness and the criminal justice system. An article on the role played by addiction can be found here.

We also discussed the clinical examination for airway obstruction, focusing on Dr. Sharon Straus' practical approach outlined here. Essentially, the combination of (all three) 1) self reported COPD, 2) Forced expiratory time >9 seconds, and 3) wheeze on auscultation had a positive likelihood ration (see here for definition) of 59, essentially ruling in COPD. Patients with none of the three findings had a negative LR of 0.3, effectively ruling it out.

Thursday, October 21, 2010

HIV, Splenomegaly & Lymphoma


Today we discussed the case of an HIV positive man presenting with "L flank pain" found to have anemia, splenomegaly, and a left renal vein thrombosis.

There are many learning points from this case:

The differential diagnosis for splenomegaly:
  • Reticuloendothelial hyperplasia (chronic hemolysis, sickle cell, thal major)
  • Infection-related hyperplasia (including HIV, EBC, CMR, TB, malaria, MAI)
  • Autoimmune hyperplasia (SLE, RA - known as Felty's syndrome when neutropenia present)
  • Malignancies (myeloproliferative, leukemia, lymphoma, myeloma, amyloid)
  • Granulatomous disease (Sarcoid, TB)
  • Congestion (Cirrhosis, CHF, portal or splenic vein thrombosis, schistosomiasis)
  • Infiltration (storage diseases)
The rational clinical exam for splenomegaly (see here) that suggests that palpation and percussion are most helpful if your pretest probability is >10%

The clear association between HIV and lymphoma, most commonly high-grade B-cell non-Hodgkin's lymphoma. However, increasingly we are seeing more and more Hodgkin's lymphomas in HIV+ patients as well. See here for more details.

Hyponatremia and psoas abscess


Last week we discussed a patient with chronic liver disease secondary to alcohol presenting with gram-negative bacteremia, hyponatremia, and a psoas abscess. We focused mostly on the diagnosis and management of hyponatremia.

Hyponatremia: there are a few questions you must ask yourself:

1. Is it real?
  • Think of other osmoles - glucose, mannitol, paraproteins
2. Is the urine reponse appropriate - ie what is the Urine Osmolality?
  • If low, the urine is appropriately dilute
  • If > 100, it is inappropriately concentrated - there must be ADH on board
3. What is the patients volume status?
  • Determine if hypo-, iso-, or hypervolemic
  • Physical exam is helpful in the extremes, but interobserver reliability is low.
  • In the absence of diuretics, Urine Na can be helful - less than 20 suggests the kidneys are avidly reabsorbing Na, so the patient is either hypovolemic or has low effective circulating volume but hypervolemic. The physical exam is helpful in differentiating these states.
  • If the patient is on a diuretic, the fractional excretion of urea can be used (value >35% is euvolemic). Defined as Fractional Excretion of Urea (FEUrea) = (SerumCr * UUrea ) / (SerumUrea x UCr) %.
Once you have answered these three questions, you can accurately classify their hyponatremia as hypovolemic (renal or extra-renal losses, the urine Na can help determine), euvolemic (SIADH based on your urine Osm, adrenal insufficiency, hypothyroidism, or primary polydipsia/low solute diet if the urine is appropriately dilute), or hypervolemic (ie liver, cardiac, or renal failure).

In managing hyponatremia, it is essential to avoid overly rapid correction which can cause osmotic demyelination syndrome. Treatment modality will depend on the patients volume status. There are very few indications for hypertonic saline - essentially only if the patient is seizing and you think it's related to their sodium. Remember to monitor the sodium level frequently as well as the urine output - once you have volume repleted the patient, the stimulus for ADH gets 'shut off', resulting in sudden outpouring of dilute urine which can cause a sudden (too quick!) rise in your serum sodium.

Here is a brief review of hyponatremia.

If you are interested in learning more about psoas absecesses, take a look at this review.

Wednesday, October 6, 2010

Fever of Unknown Origin


After a month of junior attending, the blog is back! On Tuesday we discussed an interesting case of fever of unknown origin (FUO). FUO is a clinical entity that is defined as a T > 38.3 on several occasions for >3 weeks, the etiology of which remains unclear after 1 week of diagnosis.

A home-grown review article (see here) highlights the importance of approaching these patients methodically. Of note, this algorithm does not apply to patients who are HIV+ or have a known malignancy, or to children. Up to 20% of patients with FUO remain undiagnosed. Among those in whom a diagnosis is found, 25-30% are found to have infectious causes, 20-30% are found to have inflammatory causes, and 15-20% have malignant causes. The remainder belong to the "other" category - see below.

Infectious Causes of FUO
Bacterial
Endocarditis (apply Duke criteria, think of HACEK organisms and Q fever)
Abscesses (especially intra-abdominal - consider CT)
Dental abscesses, sinusitis
Osteomyelitis
Mycobacteria (TB)
Spirochetes (Syphilis - get VDRL, Lyme disease)

Viral
HIV, HBV, HCV, EBV, CMV

Fungal
Aspergillus, histoplasmosis, coccidiodomycosis, blastomycosis, disseminated candida

Parasites
Malaria, schistosomiasis, Chagas

Inflammatory Causes of FUO
SLE, RA, PMR, Sjogren's
Vasculitis (GCA, WG, PAN)
Behcet's Disease
Sarcoid, IBD, Still's Disease

Malignant Causes of FUO
Leukemia, Lymphoma
Renal Cell CA
Hepatocellular CA
Colorectal CA

Other Causes of FUO
Drug fever
DVT/PE
Subacute thyroiditis
Familial mediterranean fever
Factitious
Disorder of hemostasis

Key principles and approach (see article link above for a great algorithm):
1. Take a thorough Hx and P/E to point you to a focus: thorough ROS, travel/medication/sexual/occupational history, infectious risk factors
2. Stop all non-essential medications and fight the urge to treat empirically
3. Basic investigations: CBC + diff + film, Cr, LFTs, anti-HCV, HBsAg, anti-HBs, Blood cultures x3, UA and urine culture, HIV, CMV/EBV serology may be helpful, ANA, RF, LDH, CXR
4. Abdo CT to rule out abscess and look for tumour, nodes +/- Technitium-based nuclear scan to identify a focus
5. Apply duke criteria and obtain echo, blood cultures
6. Leg dopplers to rule out DVT
7. If older than 50, get temporal artery biopsy to rule out GCA
8. Liver bx can be helpful if LFTs abnormal